
Nursing Care Plan

Search Here

Nursing Care Plan for Tuberculosis TB

Tuberculosis (TB) is a bacterial infection caused by a germ called Mycobacterium tuberculosis. The bacteria usually attack the lungs, but they can also damage other parts of the body. TB spreads through the air when a person with TB of the lungs or throat coughs, sneezes or talks. If you have been exposed, you should go to your doctor for tests. You are more likely to get TB if you have a weak immune system.

Symptoms of TB in the lungs may include
  • A bad cough that lasts 3 weeks or longer
  • Weight loss
  • Coughing up blood or mucus
  • Weakness or fatigue
  • Fever and chills
  • Night sweats
If not treated properly, TB can be deadly. You can usually cure active TB by taking several medicines for a long period of time. People with latent TB can take medicine so that they do not develop active TB.nlm.nih.gov

Centers for Disease Control and Prevention

Tuberculosis TB Nursing Care Plan


Nursing Care Plan for Pulmonary Tuberculosis
Nursing Assessment
  1. IdentityThe assessment includes name, age, sex, religion, ethnicity, education, employment and housing clients. In addition, it is necessary also reviewed the name and address of responsible person, and its relationships with clients.
  2. History Formerly Disease
    Review the history of the disease who had suffered from childhood to adulthood, including the experience of surgery or injury resulting from accidents, it is important to expose the client health issues that may cause more severe complications of the disease is tuberculosis.
  3. Disease History Now
    • Main Complaint
      Complaints night fever, night sweats, coughing up phlegm / bleeding, difficulty breathing, fatigue, night sweats, decreased appetite, weight loss.
    • History of Disease
      How long illness experienced, the things that lighten / aggravate the disease.
    • Efforts taken to resolve complaints.
  4. Health Patterns
    1. Activity / Rest
      Clients may experience areduction in weakness ,shortness of breath due to work, difficulty sleeping at night ,night fever ,chills or sweating . Characterized by muscle weakness, pain, and shortness (advanced stage).
    2. Ego Integrity
      Clients can experience stress, financial problems, feeling helpless / hopeless marked denial, anxiety, fear, easily aroused.
    3. Nutrition / fluid
      Clients may complain of poor appetite, unable to digest, weight loss. Marked by poor skin turgor, dry / scaly skin, loss of muscle / subcutaneous fat loss.
    4. Pain / Leisure
      Increased chest pain due to recurrent cough, marked behavioral distraction and anxiety.
    5. Respiratory
      Clients complain of cough, productive or non-productive, short breath, a history of tuberculosis or exposure to an infected individual. Characterized by increased frequency, deaf percussionist and a decrease fremitus, breath sounds: decreased, tubular and / or pectoral whisper above the lesion area. Krekels recorded over the lung during inspiration stale quickly after a short cough. Characteristics of green sputum / purulent, mukoid yellow, or blood spots, mental changes (advanced stage).
    6. Social interaction
      Clients feel isolated / rejection due to communicable diseases, unusual patterns of change in responsibilities or change in physical capacity to perform the role.
    7. Counseling / learning
      Characterized by a family history of suffering from tuberculosis, the general inability / poor health status, failed to improve / recurrence of disease and do not want to participate in therapy.
    8. (Doenges, 2000, p. 240-241)
Nursing Diagnosis for Pulmonary Tuberculosis
  1. Ineffective Airway Clearance related to :
    • thick secretions
    • weakness, bad cough efforts
    • edema, tracheal / pharyngeal

  2. Impaired Gas Exchange related to :
    • reduced effectiveness of lung surface
    • atelectasis
    • alveolar capillary membrane damage
    • thick secretions
    • bronchial edema

  3. Risk For Infection and spread of infection related to :
    • decreased immune system
    • cilia function declines
    • secretions that settle
    • tissue damage due to the spread of infection
    • malnutrition
    • contaminated by the environment
    • lack of knowledge about infectious germs

  4. Imbalanced Nutrition Less than Body Requirements related to :
    • fatigue
    • coughing frequently
    • the production of sputum
    • dyspnea
    • anorexia
    • impairment of financial capability
  5. Knowledge Deficit : about the condition, treatment, prevention relating to :
    • nothing is explained
    • wrong interpretation
    • the information obtained is incomplete / inaccurate
    • lack of knowledge / cognitive.

Nursing Care Plan for Asthma

Asthma is a chronic disease that affects your airways. Your airways are tubes that carry air in and out of your lungs. If you have asthma, the inside walls of your airways become sore and swollen. That makes them very sensitive, and they may react strongly to things that you are allergic to or find irritating. When your airways react, they get narrower and your lungs get less air. This can cause wheezing, coughing, chest tightness and trouble breathing, especially early in the morning or at night.

When your asthma symptoms become worse than usual, it's called an asthma attack. In a severe asthma attack, the airways can close so much that your vital organs do not get enough oxygen. People can die from severe asthma attacks.

Asthma is treated with two kinds of medicines: quick-relief medicines to stop asthma symptoms and long-term control medicines to prevent symptoms.

NIH: National Heart, Lung, and Blood Institute


Asthma Nursing Care Plan


Assessment of nursing in asthma patients, as follows:

Past medical history:

  • Assess personal or family history of previous lung disease.
  • Assess history of allergic reaction or sensitivity to the substances / environmental factors.
  •  Assess patient's employment history.
Activities:
  • The inability to perform activities because of difficulty breathing.
  • The decline in the ability / improvement needs help doing daily activities.
  • Sleep in a sitting position higher.
Respiratory:
  • Dipsnea at rest or in response to activity or exercise.
  • Breath worsened when the patient lay supine in bed.
  • Using the breathing aids drug, for example: raising the shoulders, widen the nose.
  • The existence of wheezing breath sounds.
  • The recurrent coughing.
Circulation:
  • There is an increasing blood pressure.
  • There is an increasing frequency of heart.
  • The color of skin or mucous membranes normal / gray / cyanosis.
  • Flushing or sweating.
Integrity ego:
  • Anxiety
  • Fear
  • Sensitive stimulation
  • Fidget

Nutrient intake:

  • Inability to eat due to respiratory distress.
  • Weight loss due to anorexia.

Social relations:

  • The limited physical mobility.
  • Hard talk
  • The existence of dependence on others.
Sexuality:
  • Decrease in libido


Nursing Diagnosis, Nursing Interventions, Nursing Care Plan for Asthma

Impaired Gas Exchange

Related to :
  • Altered oxygen supply,
  • obstruction of airways by secretions,
  • bronchospasm
Nursing Interventions :
  • Monitor vital signs
  • Monitor and graph serial ABGs and pulse oximetry.
  • Administer medications as indicated
  • monitor skin and mucous membrane color.

Ineffective Airway Clearance

Related to :
  • Bronchospasm,
  • Increased production of secretions,
  • Retained secretions, thick, viscous secretions
Nursing Interventions :
  • Assist client to maintain a comfortable position.
  • Evaluate respiratory rate/depth and breath sounds.
  • Encourage/instruct in deep-breathing and directed coughing exercises.
  • Keep environmental free from sources of allergen such as dust, smoke, and feather pillows to a minimum according to individual situation.

Nursing Care Plans for Fluid Volume Deficit

Definition : Decreased intravascular, interstitial, and or intracellular fluid.

Related Factors:
Active fluid volume loss; failure of regulatory mechanisms

Deficient Fluid volume Characteristics : Decreased urine output, increased urine concentration, weakness, sudden weight loss, decreased venous filling, increased body temperature, decreased pulse volume or pressure, change in mental state, elevated hematocrit, decreased skin or tongue turgor; dry skin/mucous membranes, thirst, increased pulse rate, decreased blood pressure.

Deficient Fluid volume Outcomes
  • Maintains urine output more than 1300 ml/day (or at least 30 ml/hr)
  • Maintains normal blood pressure, pulse, and body temperature
  • Maintains elastic skin turgor; moist tongue and mucous membranes; and orientation to person, place, time
  • Explains measures that can be taken to treat or prevent fluid volume loss
  • Describes symptoms that indicate the need to consult with health care provider

NOC Outcomes (Nursing Outcomes Classification): Suggested NOC Labels
  • Fluid Balance
  • Hydration
  • Nutritional Status: Food and Fluid Intake

NIC Interventions (Nursing Interventions Classification) Suggested NIC Labels
  • Fluid Management
  • Hypovolemia Management
  • Shock Management: Volume

Nursing Interventions Nursing Care Plans for Fluid Volume Deficit
  • Asses:
    • Moistness of mucous membrane and skin turgor and chart findings.
    • Intake and output.
    • Orthostatic hypotension QD.
    • Daily weights using same scale.
    • Labs: HCT, BUN, Specific gravity, Sodium
  • Encourage fluid intake.

  • Assist patient with drinking if necessary.

  • Explore patient's understanding of etiological factors and provide necessary teaching.

Nursing Care Plan for Diarrhea

Definition: Passage of loose, unformed stools

Related Factors:
  • Psychological
  • High stress levels and anxiety
  • Situational
  • Alcohol abuse, toxins, laxative abuse, radiation, tube feedings , adverse effects of medications, contaminants, travel
  • Physiological
  • Inflammation, malabsorption, infectious processes, irritation, parasites

As evidenced by

Major:
  • Loose liquid stools and/or:
  • Frequency
Minor:
  • Urgency
  • Cramping/abdominal pain
  • Hyperactive bowel sounds
  • Increase of fluidity or volume of stools

Outcomes
  • Defecates formed, soft stool every day to every third day
  • Maintains a rectal area free of irritation
  • States relief from cramping and less or no diarrhea
  • Explains cause of diarrhea and rationale for treatment
  • Maintains good skin turgor and weight at usual level
  • Contains stool appropriately (if previously incontinent)

Nursing Interventions Nursing Care Plan for Diarrhea
  • Assess abdomen for distention, bowel sounds, pain.

  • Identify factors that contribute to diarrhea.

  • Record color, odor, amount and frequency of stool.

  • Instruct patient in:
    • diet
    • medication usage
    • S/S of diarrhea to watch for requiring medical attention
    • discontinuing solids
    • offer clear liquids.

Nursing Care Plan for Constipation

Definition: A decrease in a person's normal frequency of defecation, accompanied by difficult or incomplete passage of stool and/or passage of excessively hard, dry stool

Defining Characteristics: Change in bowel pattern; bright red blood with stool; presence of soft paste-like stool in rectum; distended abdomen; dark, black, or tarry stool; increased abdominal pressure; percussed abdominal dullness; pain with defecation; decreased volume of stool; straining with defecation; decreased frequency; dry, hard, formed stool; palpable rectal mass; feeling of rectal fullness or pressure; abdominal pain; unable to pass stool; anorexia; headache; change in abdominal growing (borborygmi); indigestion; atypical presentation in older adults (e.g., change in mental status, urinary incontinence, unexplained falls, elevated body temperature); severe flatus; generalized fatigue; hypoactive or hyperactive bowel sounds; palpable abdominal mass; abdominal tenderness with or without palpable muscle resistance; nausea and/or vomiting; oozing liquid stool.


Related To:
  • Malnutrition
  • Metabolic and endocrine disorders
  • Sensory/motor disorders
  • Stress
  • Immobility
  • Inadequate diet
  • Irregular evacuation pattern

As evidenced by


Major: Hard formed stool and/or defecation occurs fewer than three times per week.
Minor:
  • Decreased bowel sounds.
  • Reported feeling of rectal fullness or pressure around rectum.
  • Straining and pain on defecation.
  • Palpable impaction.

Outcome

The patient will:
  • Have soft formed stool.
  • Patient and/or significant other will verbalize an understanding of method for preventing and/or treating constipation.

Nursing Interventions for Constipation
  • Assess abdomen for distention, bowel sounds.
  • Assess bowel elimination.
  • Asses factors responsible for constipation :
    • stress
    • discomfort
    • sedentary lifestyle
    • laxative abuse
    • debilitation
    • lack of time/privacy
    • drug side effect

  • Promote corrective measures :
    • review daily routine
    • provide privacy/time
    • provide comfort
    • encourage adequate exercise

Nursing Care Plan for Stroke

Nursing Care Plan for Stroke

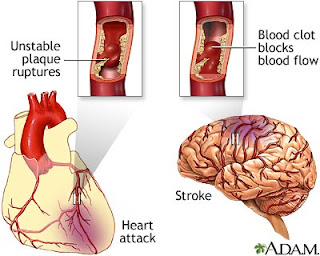
A stroke, previously known medically as a cerebrovascular accident (CVA), is the rapidly developing loss of brain function(s) due to disturbance in the blood supply to the brain. This can be due to ischemia (lack of blood flow) caused by blockage (thrombosis, arterial embolism), or a haemorrhage (leakage of blood). As a result, the affected area of the brain is unable to function, which might result in an inability to move one or more limbs on one side of the body, inability to understand or formulate speech, or an inability to see one side of the visual field.

A stroke is a medical emergency and can cause permanent neurological damage, complications, and death. It is the leading cause of adult disability in the United States and Europe and the second leading cause of death worldwide. Risk factors for stroke include old age, hypertension (high blood pressure), previous stroke or transient ischemic attack (TIA), diabetes, high cholesterol, cigarette smoking and atrial fibrillation. High blood pressure is the most important modifiable risk factor of stroke.


Stroke

Stroke Nursing Assessment
  1. Changes in level of consciousness or responivitas as evidenced by the movement, refused to change its position and response to stimulation, oriented to time, place and person
  2. Whether or not a volunteer or involuntary limb movements, muscle tone, posture, and head position.
  3. Neck stiffness.
  4. The opening of the eyes, the comparative size of the pupil, and pupil reaction to light and ocular position.
  5. The color of the face and extremities, skin temperature and humidity.
  6. The quality and frequency of pulse, respiration, arterial blood gases as indicated, body temperature and arterial pressure.
  7. Ability to speak
  8. The volume of fluid you drink and the volume of urine released every 24 hours.

Stroke Nursing Diagnosis
  1. Impaired verbal communcation
  2. Impaired physical Mobility
  3. Anxiety [specify level]
  4. Deficient knowledge regarding diagnosis, prognosis, and treatment options
  5. Risk for disturbed Body Image
  6. Risk for ineffective Sexual Pattern
  7. Self-Care Deficit [specify]
  8. Disturbed Sensory Perception (specify)
  9. Disturbed Thought Processes
  10. Risk for Injury/Trauma

Nursing Care Plan for Anemia


NCP for Anemia
Nursing Care Plan for Anemia

NCP for Anemia


Anemia

Anemia is a medical condition in which the red blood cell count or hemoglobin is less than normal. The normal level of hemoglobin is generally different in males and females. For men, anemia is typically defined as hemoglobin level of less than 13.5 gram/100ml and in women as hemoglobin of less than 12.0 gram/100ml. These definitions may vary slightly depending on the source and the laboratory reference used.

Anemia Symptoms

Clinical symptoms that appear to reflect dysfunction of various systems in the body such as decrease in physical performance, impaired neurologic (nerve), which is manifested in changes in behavior, anorexia (emaciated body), and abnormal cognitive development in children. Often, too, growth abnormality, epithelial dysfunction, and reduced gastric acidity.

An easy way to know anemia with 5 signs: weak, tired, lethargic, tired, negligent. If it appears five of thesesymptoms, we can be sure a person has anemia. Another symptom is the appearance of sclera (white color on the lower eyelid).

Anemia can cause fatigue, weakness, lack of energy and the head was floating. If the anemia gets worse, can cause a stroke or heart attack.
Source : http://signssymptoms.blogspot.com/2011/04/anemia-symptoms.html

Nursing Assessment for Anemia
Assessment of patients with anemia (Doenges, 1999) include :
  1. Activity / rest
    Symptoms :
    fatigue, weakness, general malaise. Lost productivity: a reduction in enthusiasm for work. Low exercise tolerance. The need for sleep and rest more.
    Signs :
    tachycardia / takipnae; dyspnea during work or rest. Lethargy, withdrawn, apathetic, lethargic, and less interested in its surroundings. Muscle weakness, and decreased strength. Ataxia, the body is not upright. Shoulders down, slumped posture, slow, and other signs that indicate fatigue.
  2. Circulation
    Symptoms :
    A history of chronic blood loss, such as chronic gastrointestinal bleeding, heavy menstruation, angina, CHF (due to excessive cardiac work). History of chronic infective endocarditis. Palpitations (tachycardia compensation).
    Signs :
    Blood pressure: systolic to diastolic steady improvement, and widening pulse pressure, postural hypotension. Dysrhythmias: ECG abnormality, ST segment depression and T wave leveling or depression; tachycardia. The sound of the heart: systolic murmur. Extremity (color): pale skin and mucous membranes (conjunctiva, mouth, pharynx, lips) and the base of the nail. (Note: in black patients, white may appear to be grayish). Leather like waxy, pale or bright lemon yellow. Sclera: blue or pearly white. Slow capillary filling (decreased blood flow to the capillary and vasoconstriction compensation) nails: easily broken, shaped like a spoon (koilonikia). Hair: dry, easily breaking, thinning, gray hair grow prematurely.
  3. Integrity ego
    Symptoms :
    Religious beliefs / cultural influence treatment options, such as refusal of blood transfusions.
    Signs :
    depression.
  4. Elimination
    Symptoms :
    A history of pyelonephritis, kidney failure. Flatulen, malabsorption syndrome. Hematemesis, stool with fresh blood, melena. Diarrhea or constipation. Decrease in urine output.
    Signs :
    Abdominal distension.
  5. Food / fluid
    Symptoms :
    Decreased dietary input. Painful mouth or tongue, difficulty swallowing (pharyngeal ulcers). Nausea / vomiting, dyspepsia, anorexia. The presence of weight loss. Never satisfied to chew or sensitive to ice, dirt, corn flour, paint, clay, and so forth.
    Signs :
    Tongue looks red meat / subtle deficiency of folic acid and vitamin B12. Dry mucous membranes, pale. Skin turgor: ugly, dry, looks shriveled / lost elasticity. Stomatitis and glositis (deficiency status). Lips: selitis, such as inflammatory lips with the corner of his mouth cracked.
  6. Neurosensori
    Symptoms :
    Headache, throbbing, vertigo, tinnitus, inability to concentrate. Insomnia, decreased vision, and shadows on the eyes. Weakness, poor balance, unsteady legs, paresthesias hands / feet; klaudikasi. The sensation of being cold.
    Signs :
    Sensitive to stimuli, anxiety, depression tend to sleep, apathy. Mental: not able to respond, slow and shallow. Ophthalmic: hemoragis retina. Epitaksis: bleeding from the holes (aplastic). Impaired coordination, ataxia, decreased sense of vibration, and position, positive Romberg sign, paralysis.
  7. Pain / comfort
    Symptoms: abdominal pain, headache
  8. Breathing
    Symptoms :
    A history of tuberculosis, lung abscess. Short of breath at rest and activity.
    Signs :
    Tachypnoea, orthopnea, and dyspnea.
  9. Security
    Symptoms :
    A history of work exposure to chemicals,. History of exposure to radiation, either to treatment or accident. History of cancer, cancer therapy. Not tolerant of cold and heat. Previous blood transfusion. Impaired vision, poor wound healing, frequent infections.
    Signs :
    A low fever, chills, night sweats, general lymphadenopathy. Ptekie and ekimosis(aplastic).
  10. Sexuality
    Symptoms :
    Changes in menstrual flow, such as menorrhagia or amenorrhea. Lost libido (male and female). Imppoten.
    Signs :
    Pale vaginal walls.
Related Articles :

Nursing Diagnosis For Anemia

Nursing Diagnosis for Anemia
  1. Risk of infection related to an inadequate defense, the secondary (decrease in hemoglobin leucopenia, or a decrease in granulocytes (inflammatory response depressed)).
  2. Imbalanced nutrition: Less than body requirements related to the failure to digest or inability to digest the food / nutrient absorption necessary for the formation of red blood cells…….

Nursing Interventions For Anemia

  1. Assess the level of client activity
    Rational: To know the client and the activities undertaken to determine the next intervention.
  2. Put the tools needed client
    Rational: To assist clients in meeting their needs.
  3. Assist patients in active and passive exercises……..


5FMWKASQYQ8N